


< !--cell-- >
< !--end grid-x-->


Rural Hospital Closures and the Fifth District
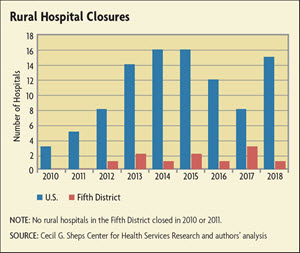
Since 2010, some 106 hospitals in American rural areas closed their doors. The closures took place at a time when population and employment growth is more skewed than ever toward our biggest cities, when finding access to health care in more isolated areas is as difficult as it has ever been, and when the loss of an anchor institution, such as a hospital, can have devastating effects on the community and economic development of rural households. Why do we see hospitals in rural areas closing at a higher rate than at any time since the mid-1980s? What are the economics that hospitals in rural areas are facing? And what may be the consequences of the loss of these anchor institutions for communities?
The share of rural hospitals that have closed exceeds that of hospitals in urban areas, and rural hospital closures have accelerated. (See chart below.) Of the 106 hospitals that closed, two-thirds were in the South — as defined by the census regions West South Central, East South Central, and South Atlantic — and of these, 12 were in the Fifth Federal Reserve District. ("Closing" here means ceasing to provide general, short-term, acute inpatient care.) According to a Government Accountability Office (GAO) report, rural hospitals in the southern United States represented 38 percent of rural hospitals in 2013 but 77 percent of the closures from 2013 through 2017. In the Fifth District, although North Carolina, South Carolina, and Virginia had the highest number of hospital closures, an analysis by David Mosley and Daniel DeBehnke of Navigant used variables such as total operating margin, days of cash on hand, and debt-to-capitalization ratio to determine that West Virginia had the highest number and share of rural hospitals at high financial risk of closure.
What's "Rural"?
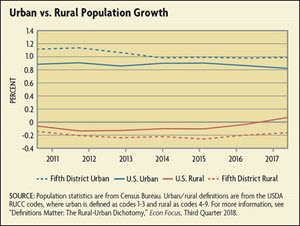
In this article, except where otherwise noted, "rural" is defined using the Federal Office of Rural Health Policy's (FORHP) definition, which includes any of three areas: (1) a county outside of a metropolitan area; (2) a county in a metropolitan area but with a rural-urban commuting area code of 4 or higher; or (3) one of the 132 large and sparsely populated census tracts with a rural-urban commuting area code of 2 or 3 — these tracts are at least 400 square miles in an area with a population density of no more than 35 people per square mile. In this way, FORHP attempts to classify "rural" in a way that accounts for distance to services and sparse population. (For more information on ways to classify urban and rural areas, see "Definitions Matter: The Rural-Urban Dichotomy," Econ Focus, Third Quarter 2018.)
Source: https://www.hrsa.gov/rural-health/about-us/definition/index.html
Critical Access Hospitals
"Critical Access Hospital" is a designation given to certain rural hospitals by the Centers for Medicare and Medicaid Services with the intention of reducing the financial vulnerability of those hospitals and keeping essential medical services (and thus access to health care) in rural communities. There are conditions that a hospital has to meet to obtain CAH status (for example, it has to be more than 35 miles from another hospital and provide 24/7 emergency services) and the benefits of CAH status (for example, cost-based reimbursement for Medicare services).
 Download article
Subscribe to Econ Focus
Receive an email notification when Econ Focus is posted online.
By submitting this form you agree to the Bank's Terms & Conditions and Privacy Notice.
Contact Us